

Menopause Is Not the End of Womanhood, but a Transition That Your Body Needs You to Understand
Many women begin to notice that their bodies no longer feel the same in their late 40s to early 50s. Some experience irregular periods—heavier in some months and absent in others. Some have difficulty falling asleep despite being exhausted all day. Others wake during the night because of hot flashes and night sweats that soak their clothes. Some become more irritable, experience palpitations or anxiety, or feel that their emotions fluctuate without understanding why.
These may be signs of the transition into menopause, medically known as perimenopause and menopause.
Menopause is not a serious disease, an abnormality, or something to be ashamed of. It is a natural stage of a woman’s life caused by a gradual decline in ovarian function, leading to changes in estrogen and progesterone levels. Some symptoms may be mild and resolve on their own, while others can significantly affect sleep, work, relationships, bone health, cardiovascular health, and overall quality of life.
NICE states that menopause care should focus on identifying symptoms, providing information and support, and selecting treatment appropriate for each individual rather than expecting women to simply endure their symptoms without options.
What Is Menopause?
The term menopause refers to the permanent cessation of menstruation and is generally diagnosed after 12 consecutive months without a menstrual period, when this is not caused by pregnancy, medication, or another medical condition. Perimenopause is the period leading up to menopause, when hormone levels begin to fluctuate, menstrual cycles become irregular, and symptoms such as hot flashes, insomnia, and mood changes may begin.
The European Society of Endocrinology describes menopause as a spectrum extending from perimenopause through postmenopause. In women over 45, diagnosis is usually based primarily on symptoms and menstrual patterns, without the need for hormone testing in every patient.
Natural menopause usually occurs between approximately 45 and 55 years of age. However, some women may enter menopause earlier because of genetic factors, ovarian surgery, chemotherapy, radiation therapy, certain autoimmune diseases, or reduced ovarian function. Loss of ovarian function before age 40 is referred to as premature ovarian insufficiency and should be medically evaluated because it can affect bone health, cardiovascular health, and long-term well-being.
What Are Hot Flashes and Why Do They Occur?
Hot flashes are among the most common symptoms during the menopausal transition. A person may suddenly feel intense warmth in the face, neck, chest, or throughout the body. Sweating, palpitations, facial flushing, or a sensation that body temperature is difficult to control may also occur. Episodes typically last several minutes but can happen many times per day. When they occur at night, they are known as night sweats and can be an important cause of disrupted sleep.
Hot flashes are associated with declining estrogen levels and changes in the brain’s temperature-regulating mechanisms, making the body more sensitive to relatively small changes in temperature. Some women experience symptoms for only a few months, while others continue to experience them for several years. Severity varies considerably between individuals.
NAMS states that hormone therapy is the most effective treatment for vasomotor symptoms such as hot flashes and night sweats. However, treatment should be individualized according to age, time since menopause, underlying health conditions, individual risks, and patient preferences.
Why Can Menopause Cause Insomnia?
Insomnia during menopause is not caused by stress alone. Some women wake because of night sweats, while others wake during the night and cannot fall asleep again. Some have lighter, less restorative sleep or remain tired despite spending enough hours in bed. Poor sleep may contribute to mood changes, difficulty concentrating, headaches, easier weight gain, and difficulty managing existing health conditions.
Several factors may contribute simultaneously, including nighttime hot flashes, anxiety, depression, sleep apnea, frequent urination, joint or muscle pain, and age-related changes in sleep patterns. Therefore, treatment of menopausal insomnia should not automatically begin with sleeping medication. The underlying cause should first be evaluated.
If insomnia is driven by hot flashes, controlling vasomotor symptoms may improve sleep. If insomnia occurs together with loud snoring, repeated awakenings, interrupted breathing, or excessive daytime sleepiness, evaluation for sleep apnea may be appropriate. If there is persistent sadness, loss of interest, frequent crying, or thoughts of not wanting to live, evaluation for depression is important.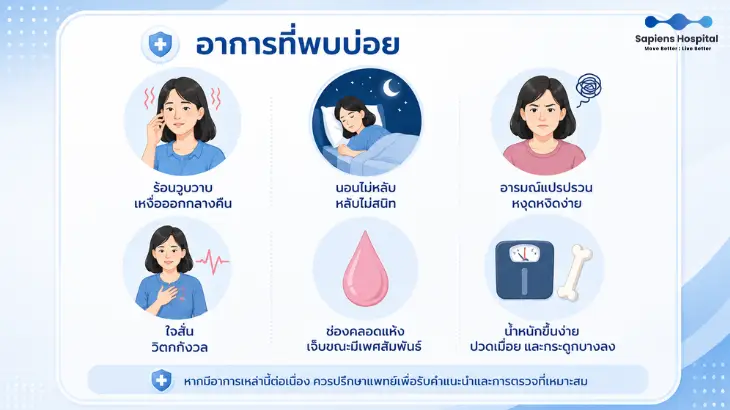
Are Mood Changes, Anxiety, and Palpitations Really Caused by Menopause?
Many women going through menopause feel that they have changed, even though they do not want to become more irritable or anxious. Hormonal fluctuations, insufficient sleep, work demands, family responsibilities, caring for aging parents, concerns about physical changes, and accumulated stress can all contribute to emotional instability during this period.
Common symptoms include irritability, tearfulness, palpitations, anxiety, reduced concentration, memory difficulties, or reduced self-confidence. These symptoms may be associated with menopause, but they should not automatically be attributed to menopause because thyroid disease, anemia, heart disease, abnormal blood pressure, depression, or medication side effects can produce similar symptoms.
If you experience severe palpitations, chest pain or tightness, unusual shortness of breath, fainting, rapid unexplained weight loss, marked tremors, or depression that significantly affects daily life, you should see a doctor to rule out other causes rather than assuming that menopause is responsible.
Other Menopausal Symptoms That Are Often Overlooked
In addition to hot flashes, insomnia, and mood changes, menopausal women may experience vaginal dryness, pain during sexual intercourse, burning or itching around the genital area, painful urination, frequent urination, or urinary leakage. These symptoms are related to declining estrogen levels in the genital and urinary tissues and are collectively known as genitourinary syndrome of menopause.
ACOG states that estrogen therapy, including systemic and local forms, can help relieve vaginal dryness. The appropriate treatment depends on symptoms, individual risks, and clinical indications.
Bone health is another important consideration. After menopause, declining estrogen can accelerate bone loss, particularly during the early postmenopausal years. Women with risk factors such as very low body weight, previous fragility fractures, long-term steroid use, a family history of hip fracture, smoking, excessive alcohol consumption, or early menopause should discuss assessment for low bone density or osteoporosis with their doctor.
Do You Need Hormone Tests to Know Whether You Are in Menopause?
Many women want hormone tests to confirm whether they are entering menopause. However, in women over 45 who have changes in menstrual patterns and symptoms consistent with menopause, diagnosis is usually based on medical history and symptoms, and hormone testing is not necessary for everyone. The European Society of Endocrinology states that biochemical testing for the diagnosis or management of menopause in women over 45 is generally unnecessary.
However, if menstrual abnormalities or menopause-like symptoms occur before age 40, additional investigation is appropriate to assess for premature ovarian insufficiency and other possible causes. Between ages 40 and 45, hormone testing may be considered in selected cases at the doctor’s discretion, particularly when symptoms are unclear or fertility concerns are also present.
Managing Menopause Starts with Understanding Your Body
Good menopause care is not about medication alone. It begins with understanding how your body is changing, which symptoms are common, which require further evaluation, and which aspects of daily life may be making symptoms worse.
Some women notice that hot flashes become more frequent after alcohol, coffee, spicy foods, exposure to heat, stress, or inadequate sleep. Keeping a daily record of symptoms and possible triggers can help identify patterns.
Maintaining a regular sleep schedule, reducing screen use before bedtime, keeping the bedroom cool, wearing breathable clothing, exercising regularly, practicing breathing or relaxation techniques before sleep, and reducing alcohol consumption may help reduce symptoms in some women. These approaches do not eliminate symptoms for everyone, but they provide a useful foundation that may also improve the effectiveness of other treatments.
Diet and Exercise During Menopause
Menopause is a period when body composition may change more easily. Abdominal fat may increase, muscle mass may decline, and weight gain may occur more easily even when food intake has not changed. A balanced diet should therefore emphasize adequate protein, vegetables and fruits, whole grains, and healthy fats while limiting sugar, sweetened beverages, highly processed foods, and alcohol.
Exercise should include appropriate brisk walking, swimming, cycling, or other aerobic activities, together with weight training or resistance exercise to maintain muscle mass and balance training to reduce the long-term risk of falls. Exercise does more than help manage body weight; it can also support mood, sleep, blood pressure, blood glucose control, and bone health.
Who May Benefit from Hormone Replacement Therapy or HRT?
Hormone replacement therapy, also known as menopausal hormone therapy, is a highly effective option for women whose hot flashes, night sweats, or sleep disturbance related to vasomotor symptoms significantly affect their quality of life. NAMS states that for women younger than 60 or within 10 years of menopause who have no contraindications to hormone therapy, the benefit-risk ratio is generally favorable for treating bothersome symptoms and preventing bone loss.
An important principle is that HRT must be individualized rather than prescribed as a single standard regimen for everyone. In women who still have a uterus, estrogen alone may stimulate the endometrium, so a progestogen is generally added to protect against abnormal endometrial thickening. The European Society of Endocrinology recommends that women with a uterus who have an indication for MHT generally receive estrogen together with a progestogen, while women who have undergone hysterectomy may use estrogen alone when clinically appropriate.
Who Should Not Use Hormone Therapy Without Careful Medical Assessment?
Hormone therapy is not suitable for everyone. People with a history of breast cancer, certain endometrial cancers, venous thromboembolism, stroke, certain cardiovascular conditions, severe liver disease, or unexplained abnormal vaginal bleeding should undergo careful medical assessment before hormone therapy is considered.
If bleeding occurs after menopause, or abnormal bleeding develops while using hormone therapy, you should not adjust or stop medication on your own without medical advice. The cause of the bleeding should be evaluated because it may be related to the endometrium, polyps, uterine conditions, or the hormone regimen. NICE updated its recommendations in 2026 regarding when patients using systemic HRT should seek medical advice for bleeding, emphasizing the need for systematic follow-up.
What If You Do Not Want to Use Hormones?
Non-hormonal options are available for people who have contraindications to hormone therapy, prefer not to use hormones, or have symptoms that do not require HRT. Options may include lifestyle modification, cognitive behavioral therapy for insomnia or bothersome menopausal symptoms, and certain medications that can reduce hot flashes, including selected antidepressants, gabapentin, or medications that act on the brain’s temperature-regulation pathways where available. These treatments should be selected according to underlying medical conditions, current medications, and possible side effects and should not be self-prescribed.
The European Society of Endocrinology 2025 guideline emphasizes a holistic approach to menopause care rather than focusing solely on hormones. Management may include hormonal treatment, non-hormonal treatment, lifestyle measures, and psychosocial interventions according to individual needs.
Can Herbal Products and Supplements Help?
Many women are interested in herbal products, soy, phytoestrogens, black cohosh, and various supplements because “natural” may sound safer. However, natural does not always mean safe, and evidence regarding the effectiveness of these products varies considerably between studies.
Some supplements may affect liver function, bleeding risk, other medications, or underlying health conditions. People with liver disease, those taking anticoagulants, those with a history of hormone-sensitive cancer, or those taking multiple medications should consult a doctor before using supplements. If used, supplements should be considered supportive rather than a substitute for medical assessment when symptoms are severe or warning signs are present.
When Should You See a Doctor?
You should seek medical advice if hot flashes or night sweats interfere with sleep and work, if insomnia persists for several weeks, if mood changes affect relationships or work, or if you experience significant depression, severe anxiety, or thoughts of not wanting to live. These symptoms should not simply be endured until they become more severe.
You should also see a doctor if you experience bleeding after menopause, unusual spotting or vaginal bleeding, persistent lower abdominal pain, unexplained weight loss, severe palpitations, chest pain, shortness of breath, or hot flashes before age 40, because other conditions may need to be excluded or premature menopause may require specific management.
Health Assessment During Menopause Should Look Beyond Hot Flashes
The menopausal transition is an important opportunity to review long-term health, not just immediate symptoms. Assessment may include blood pressure, blood glucose, cholesterol, body weight, waist circumference, sleep, bone health, and age-appropriate screening for breast cancer, cervical cancer, and colorectal cancer, as well as mental health and future fall risk.
Some women seek medical attention for insomnia and are found to have high blood pressure or thyroid disease. Others assume fatigue is caused by menopause when anemia is responsible. Some believe palpitations are hormonal but actually have an underlying heart rhythm disorder. A systematic assessment can help avoid overlooking other health conditions.
Frequently Asked Questions
- At what age does menopause begin?
Symptoms commonly begin in the late 40s to early 50s, although they may start earlier or later. Menopause-like symptoms before age 40 should be medically evaluated for premature ovarian insufficiency and other possible causes. - Do hot flashes need treatment?
If symptoms are mild and do not interfere with daily life, lifestyle adjustments and avoiding triggers may be enough. If hot flashes are frequent, cause night sweats or insomnia, or significantly affect quality of life, consult a doctor because both hormonal and non-hormonal treatments are available. - Is hormone replacement therapy dangerous?
Hormone therapy has both benefits and risks and should be assessed individually. NAMS notes that risks vary according to the type and dose of therapy, duration of use, route of administration, age at initiation, time since menopause, and whether a progestogen is used. - If I still have a uterus, can I use estrogen alone?
In general, systemic estrogen should not be used alone in women with an intact uterus because it can stimulate the endometrium. A doctor will usually consider adding a progestogen when indicated to help protect against abnormal endometrial thickening. - Does menopausal insomnia require sleeping pills?
Not necessarily. The cause may be hot flashes, stress, depression, sleep apnea, or another condition. Treating the underlying cause may be more effective than relying only on sleeping medication. - Is bleeding after menopause normal?
No. Bleeding after menopause should not be assumed to be normal. If menstruation has stopped and vaginal bleeding occurs again, you should see a doctor to investigate possible causes involving the endometrium, polyps, or other conditions. - If I do not want hormones, can I use natural methods?
Good sleep habits, exercise, weight management, reducing alcohol, avoiding triggers, and managing stress may help some people. However, if symptoms are significant, consult a doctor. Several non-hormonal treatments are available and should be selected according to your individual health conditions.
Menopause is a natural transition in a woman’s life, but it does not mean that you must simply tolerate hot flashes, insomnia, night sweats, mood changes, or vaginal dryness without treatment options. These symptoms may result from hormonal changes together with physical, psychological, sleep-related, and overall health factors.
Good menopause care begins with a thorough assessment of symptoms, ruling out other conditions that may cause similar symptoms, improving sleep habits, exercising regularly, supporting bone and cardiovascular health, and considering individualized treatments such as hormone therapy, non-hormonal medications, or symptom-specific care.
Most importantly, women do not have to go through menopause alone or silently endure symptoms that interfere with their lives. Seeking medical advice and developing an appropriate care plan can help make this stage of life one in which women remain active, maintain their quality of life, and confidently protect their long-term health.
For information and appointments
Sapiens Hospital
Sapiens Hospital | Move Better : Live Better
Tel. 02-111-3703