

Sports Injuries in Children: When Should Your Child See a Sports Medicine Doctor?
Children and sports naturally go together. Running, jumping, swimming, playing football, basketball, tennis, badminton, gymnastics, or martial arts provides children with much more than stronger muscles. Sports can also help them develop discipline, confidence, social skills, an understanding of winning and losing, and goal-setting. However, childhood sports also carry a risk of injury, particularly today when many children train more intensely, compete at younger ages, repeatedly participate in the same sport throughout the year, and sometimes follow training schedules similar to those of adults even though their bodies are still growing.
Questions parents often struggle with include: “Is this injury minor enough to rest at home?” “Does my child need an X-ray?” “When can my child return to training?” and “When should we see a Sports Medicine doctor?” Some injuries may appear minor on the first day, but returning to sport too early may contribute to persistent pain, joint instability, muscle weakness, or recurrent injury.
Most importantly, children are not simply small adults. Their bones still contain growth plates, while their bones, tendons, muscles, and neuromuscular balance systems are still developing. Sports injuries in children therefore need to be assessed based on the injured area, mechanism of injury, severity, walking and weight-bearing ability, swelling and bruising, and the goal of safely returning to sport—not simply whether the child can “tolerate the pain.”
Why are sports injuries in children more common than many people realize?
Sports injuries in children can broadly be divided into two categories. The first is acute injury, such as a fall, ankle sprain, twisting injury of the knee, collision, landing on the hand, head impact, or muscle tear. The second is an overuse injury, caused by repetitive training without sufficient recovery time. Examples include anterior knee pain, pain below the knee, heel pain, shin pain, and shoulder or elbow pain from repetitive throwing, hitting, or serving.
The American Academy of Pediatrics has noted that youth sports culture has changed over recent decades. Many children specialize in a single sport at a young age, train intensively, participate year-round, or play on multiple teams at the same time. These patterns are associated with an increased risk of overuse injuries, overtraining, and burnout.
One challenge with overuse injuries is that there may be no single obvious injury event. A child may initially experience mild pain during training that disappears with rest. Later, the pain may begin earlier, last longer, continue after activity, and eventually occur during everyday activities. If parents or coaches dismiss this as ordinary soreness, the child may continue training until the problem becomes persistent.
Warning signs that mean your child should stop playing immediately
A simple rule is that if pain causes a child to change the way they run, walk, or perform a sporting movement, they should stop the activity. Children should not be encouraged to “push through the pain.” This is particularly important for younger children who may have difficulty describing symptoms. Their bodies may instead show warning signs such as limping, avoiding weight-bearing, using one arm less than usual, landing unevenly, or playing noticeably more slowly.
A child should stop playing immediately if there is rapid joint swelling after an injury, severe pain that prevents weight-bearing, a feeling that the knee or ankle is unstable, a popping sound at the time of injury, visible deformity of an arm or leg, localized bone tenderness, numbness or weakness, a cold hand or foot, skin color changes, or pain that does not improve with rest. These signs may indicate a fracture, ligament injury, joint dislocation, growth plate injury, or another condition requiring medical assessment.
For ankle injuries, the Royal Children’s Hospital Melbourne advises that assessment should distinguish an ankle sprain from a fracture and evaluate joint stability. X-rays may be considered when there is tenderness over specific bony areas or when the child is unable to bear weight both immediately after the injury and for four steps during assessment.
Which sports injuries should be assessed promptly by a doctor?
If a child cannot walk or refuses to bear weight after an injury, prompt medical assessment is appropriate rather than waiting several days. Some fractures in children may not cause obvious deformity, and a growth plate injury may require physical examination and imaging for proper assessment.
Significant or rapidly developing joint swelling, especially when accompanied by extensive bruising, should also be assessed because it may be associated with bleeding into the joint, ligament injury, meniscal injury, or fracture. If a joint becomes swollen, red, and hot with fever, or the child has severe pain without an obvious injury, urgent medical evaluation is needed because joint or bone infection may be possible.
If a child develops numbness, weakness, a cold hand or foot, pale or bluish skin, inability to move the fingers or toes, or unusually severe pain after a cast or compression bandage has been applied, urgent medical attention is required. These symptoms may involve nerves, blood vessels, or dangerous compression. The Royal Children’s Hospital Melbourne advises seeking medical attention if, after an injury or fracture treatment, the fingers or toes become very swollen, white or blue, numb, unable to move, or severely painful despite recommended pain relief.
If a child hits their head, concussion should always be considered
Sports injuries in children are not limited to the arms and legs. Head impacts during football, basketball, rugby, cycling, skateboarding, gymnastics, or martial arts may cause a concussion even when the child does not lose consciousness.
Symptoms of concussion may include headache, dizziness, nausea, blurred vision, sensitivity to light or noise, balance problems, difficulty concentrating, slowed thinking, confusion, irritability, mood changes, or sleeping more or less than usual. The CDC notes that some symptoms may not appear immediately and can develop over the hours or days following an injury.
If concussion is suspected, the child should not return to play on the same day. The CDC recommends that children with suspected concussion be evaluated by a healthcare professional and should not return to sports, cycling, skateboarding, or other activities that carry a risk of another head injury until medically cleared.
Emergency warning signs after a head injury include loss of consciousness, seizures, repeated vomiting, a progressively worsening headache, increasing drowsiness, severe confusion, slurred speech, weakness of the arms or legs, severe balance problems, unequal pupils, or marked behavioral changes. These symptoms may indicate a serious brain injury and require urgent emergency assessment.
Persistent sports-related pain should be assessed before a child becomes unable to play
Many young athletes do not see a doctor immediately after an injury but later develop persistent symptoms such as knee pain after training, heel pain while playing football, shin pain while running, shoulder pain while swimming or throwing, back pain during gymnastics, or elbow pain while playing tennis or badminton.
Pain from an overuse injury may initially occur after training, then begin during training, and eventually interfere with everyday activities. At this stage, rest alone may not be sufficient. Factors contributing to recurrence may need to be assessed, including muscle strength imbalance, movement or sporting technique, excessive training load, unsuitable footwear, playing surface, or returning to sport too early.
The AAOS describes overuse injuries in children as injuries caused by repetitive activity without sufficient recovery time. Examples include Achilles tendinitis, Osgood-Schlatter disease, jumper’s knee, Sever’s disease, shin splints, stress fractures, and throwing-related elbow injuries.
Sports-related knee pain in children
Knee pain is common in young athletes, particularly in sports involving kicking, running, jumping, rapid changes of direction, or repetitive knee bending. Children may develop Osgood-Schlatter disease, which causes pain around the bony prominence below the knee and is often aggravated by kicking, running, jumping, or kneeling. Another possibility is patellofemoral pain, which causes pain at the front of the knee or around the kneecap during activities such as climbing stairs, sitting with the knees bent for long periods, squatting, or running.
If the knee swells rapidly after twisting, there is a popping sensation, the child cannot walk, the knee feels unstable, or it locks and cannot fully bend or straighten, medical assessment is recommended. These symptoms may be associated with an anterior cruciate ligament injury, meniscal injury, cartilage injury, or fracture around the joint. Allowing a child to rest for only two or three days and then return to competition while the knee is still swollen may increase the risk of recurrent injury and delay recovery.
Ankle pain, ankle sprains, and returning to sport too soon
Ankle sprains are very common among older children and adolescents, particularly in basketball, football, badminton, volleyball, and running. A mild ankle sprain may improve with relative rest, cold therapy, compression, elevation, and gradual rehabilitation. However, significant swelling or bruising, tenderness over the bone, inability to walk, or pain lasting longer than expected should be assessed to determine whether a fracture or high ankle sprain may be present.
The Royal Children’s Hospital Melbourne describes the RICER approach—rest, ice, compression, elevation, and referral for rehabilitation or professional assessment when appropriate. Rehabilitation to improve proprioception, balance, and muscular control is particularly important for young athletes returning to sport and can help reduce the risk of recurrent ankle sprains.
An important point for parents to remember is that “pain-free” does not necessarily mean “ready to compete.” A child who returns to competition after an ankle sprain while still having poor single-leg balance, unstable landing mechanics, or pain or apprehension when running and changing direction may be at greater risk of another sprain.
Heel pain, shin pain, and stress injuries
Children who run or jump frequently may develop heel pain from Sever’s disease, which commonly occurs during periods of growth in children participating in repetitive impact sports. Children who rapidly increase their running distance or training intensity may develop shin splints, while some may develop a stress fracture, a small bone injury caused by repetitive loading.
Warning signs include highly localized bone pain, pain that increases with activity, pain at rest or at night, limping, or marked tenderness at the same location. If these symptoms occur, impact activities should be stopped and the child should be medically assessed rather than continuing to run through the pain, which could worsen the injury.
Shoulder, elbow, and wrist pain in children who play upper-limb sports
Children participating in swimming, tennis, badminton, baseball, gymnastics, volleyball, or climbing may develop shoulder, elbow, or wrist pain from repetitive use. In children whose bones are still growing, these symptoms may involve the growth plate or tendon attachment sites rather than simply representing ordinary muscle soreness.
If a child has localized pain that worsens with training, reduced strength, decreased throwing or hitting performance, limited joint movement, or numbness radiating down the arm, a Sports Medicine assessment may be appropriate. Evaluation can include sporting technique, movement patterns, scapular and shoulder strength, trunk and core control, and planning for a safe return to sport rather than simply resting and then returning to the same training pattern.
How is seeing a Sports Medicine doctor different from seeing a general doctor?
Sports Medicine assessment extends beyond determining whether there is a fracture. It may consider the mechanism of injury, type of sport, competition level, training schedule, strength, flexibility, balance, movement technique, footwear, equipment, playing surface, and readiness to return safely to sport.
For example, a child may present with knee pain, but contributing factors may include weak hip muscles, limited ankle mobility, poor landing mechanics, or excessive jumping load. A child with shoulder pain may have issues involving scapular control, core stability, or excessive hitting and serving volume. Management may therefore combine diagnosis, rehabilitation, training-load modification, and strategies to reduce the risk of recurrent injury.
The Sports Medicine approach is therefore not simply to “rest until the pain is gone.” The aim is to help children return to sport at an appropriate time with sufficient physical readiness while reducing the risk of recurrent injury as much as possible.
What examinations or tests may be needed?
Assessment begins with a detailed history, including how the injury occurred, the sport involved, the location of pain, how many days and hours per week the child trains, whether footwear or playing surfaces have changed, whether training intensity increased rapidly, whether competitions are frequent, and whether the child has previously injured the same area.
Physical examination may assess walking, running, single-leg stance, landing mechanics, joint range of motion, strength, flexibility, tenderness, joint stability, and neurological function. Imaging such as X-ray, ultrasound, or MRI is selected according to clinical indications. Not every child needs every test at the first visit, but assessment should not be unnecessarily delayed when red flags are present.
For ankle sprains, the RCH notes that MRI is not routinely used for acute diagnosis. It may be considered when pain or swelling persists for more than a month or when a syndesmosis injury is suspected during follow-up. This reflects a broader Sports Medicine principle: choose investigations according to the clinical problem, avoiding unnecessary tests while ensuring important injuries are not missed.
Initial care after a sports injury
During the first 24–48 hours after an acute injury, the child should stop activities that cause pain. Cold packs may be applied intermittently, the injured limb can be elevated when practical, and compression may be used without wrapping too tightly. Age- and weight-appropriate pain medication may be used according to a clinician’s advice or the medicine label. Avoid forceful massage, twisting, manipulation, or attempting to “put the joint back into place” yourself, especially when there is significant swelling, bruising, deformity, or severe pain.
If the child cannot bear weight, has localized bone tenderness, or significant joint swelling, medical assessment is appropriate. Avoid repeatedly making the child walk to “test” the injury. Conversely, for a minor injury that has been appropriately assessed and has no contraindication to movement, gradual movement and rehabilitation may be preferable to prolonged immobilization. This is particularly relevant for ankle sprains, where balance and muscular-control rehabilitation are important.
When is it safe to return to sport?
Return to sport should not be based solely on the number of days rested. Physical readiness is important. Ideally, the child should have no pain during normal daily activities, near-normal joint movement compared with the uninjured side, adequate strength and balance, and the ability to run, jump, change direction, or perform sport-specific movements without pain or subsequent swelling.
For concussion, extra caution is required. The CDC recommends a 6-step return-to-sport progression under the approval and supervision of a healthcare provider. Each step typically takes at least 24 hours. If symptoms return, activity should stop and the child should return to the previous symptom-free step after appropriate recovery and guidance.
For joint, muscle, or ligament injuries, returning too soon can increase the risk of recurrent injury. The AAOS advises young athletes to follow their treatment plan and obtain appropriate medical clearance before returning to sport when indicated, even if they already feel better, because premature return may worsen an injury.
Preventing injuries in young athletes
Prevention begins with balancing training, competition, rest, and recovery. Children should have appropriate breaks from repetitive year-round participation in a single sport and should avoid schedules across multiple teams that leave insufficient recovery time. Appropriate rest and participation in varied physical activities can help reduce overuse injury risk and support broader athletic development.
Children should have age-appropriate warm-ups and cool-downs rather than immediately beginning intense training. Strength, balance, flexibility, and neuromuscular-control exercises should be appropriate for their age and sport, particularly in activities involving rapid changes of direction, landing from jumps, or repetitive upper-limb movements. Adequate sleep, nutrition, hydration, and genuine rest days are also important parts of injury prevention.
Equipment should be appropriate for the sport and the child’s size. Shoes should fit properly and not be excessively worn, playing surfaces should be safe, and children should learn appropriate techniques from the beginning, including landing after a jump, changing direction, lifting, hitting, throwing, and falling safely.
What should parents ask their child after training?
Good questions are not limited to “Did you win?” or “Did you play well?” Parents can also ask: Did anything hurt today? Did it hurt during or after playing? Is the pain getting better or worse? Are you walking or running differently? Does it still hurt the next morning? Does any part of your body feel unstable or make you afraid to use it?
Some young athletes hide symptoms because they are afraid of being taken out of play, losing their position, or disappointing their team. Parents and coaches should create a culture in which reporting pain is not viewed as weakness but as responsible care for the athlete’s body. Addressing symptoms early can help prevent a minor problem from developing into a more significant injury.
Frequently Asked Questions from Parents
- My child sprained an ankle but can still walk. Is an X-ray necessary?
Not every ankle sprain requires an X-ray. However, if there is tenderness over specific bony areas of the ankle or foot, the child cannot bear weight, or cannot walk four steps during assessment, a doctor should evaluate whether an X-ray is indicated. - My child has pain after every training session, but it improves with rest. Should we see a doctor?
If the pain repeatedly returns, begins earlier during training, requires pain medication to continue training, or starts interfering with everyday activities, a Sports Medicine assessment is appropriate. This may represent an overuse injury requiring adjustment of training load and rehabilitation rather than waiting until the child can no longer play. - My child hit their head but did not lose consciousness. Can they continue playing?
No. If concussion is suspected, the child should stop playing and be assessed. Loss of consciousness is not required for a concussion, and symptoms may develop later. The CDC recommends that a child with suspected concussion should not return to sport on the same day. - Should we use heat or ice after an injury?
For an acute injury with pain, swelling, or bruising, intermittent cold therapy is commonly used during the early period. Heat may be more appropriate in selected situations involving muscle tightness or chronic symptoms. If there is significant swelling, severe pain, inability to walk, or uncertainty about the injury, seek medical assessment first.
Sports injuries should not make parents afraid to let their children participate in sports. The important point is knowing how to respond appropriately. Some minor injuries can initially be managed with basic care, but if a child cannot walk or bear weight, develops rapid joint swelling, severe pain, deformity, numbness or weakness, abnormal symptoms after a head impact, or recurrent persistent pain, medical assessment is recommended.
The goal of treatment is not simply to relieve pain, but to help the child return to sport safely, regain strength and movement, and reduce the risk of recurrent injury. For children, sport is not only about competition; it is also an important part of growth, confidence, and long-term quality of life.
If a child has severe pain, cannot walk, has a hot, red, swollen joint, visible limb deformity, numbness or weakness, or develops drowsiness, repeated vomiting, seizures, or rapidly worsening symptoms after a head injury, seek urgent medical care immediately.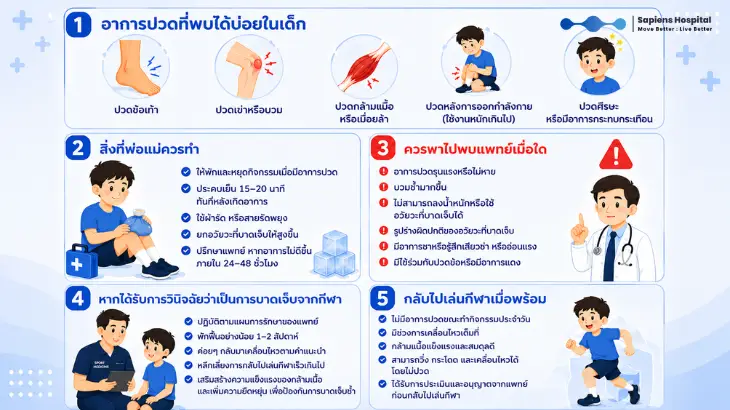
Sapiens Hospital
Move Better:Live Better
Tel. 02-111-3703
References
American Academy of Pediatrics. Sports Specialization and Intensive Training in Young Athletes.Pediatrics. Reaffirmed with updates 2021.
American Academy of Orthopaedic Surgeons. Overuse Injuries in Children. OrthoInfo.
American Academy of Orthopaedic Surgeons. A Guide to Safety for Young Athletes. OrthoInfo. Royal Children’s Hospital Melbourne. Clinical Practice Guidelines: Ankle Sprains, Emergency Department.
Centers for Disease Control and Prevention. HEADS UP: Signs and Symptoms of Concussion.
Centers for Disease Control and Prevention. HEADS UP: What to do After a Concussion. Updated September 2025.
Centers for Disease Control and Prevention. HEADS UP: Returning to Sports. Updated September 2025.